
Frozen Shoulder
Frozen shoulder, also called adhesive capsulitis, causes shoulder pain and progressive stiffness. Everyday tasks such as dressing, reaching a shelf, washing your hair or fastening clothing behind your back can become difficult. The diagnosis cannot be confirmed from symptoms or an image alone because other shoulder conditions can look similar.

What happens in frozen shoulder?
The capsule surrounding the shoulder joint becomes irritated, thickened and tight. Movement is usually restricted when you lift or rotate the arm yourself and when another person carefully moves it for you. The American Academy of Orthopaedic Surgeons notes that people with frozen shoulder have limited active and passive range of motion. Read the AAOS patient guide.
Frozen shoulder is often described in three overlapping phases. During the painful or “freezing” phase, night pain and increasing restriction may dominate. In the “frozen” phase, pain may settle while stiffness continues to affect function. During the “thawing” phase, movement gradually improves. These labels are a guide, not a fixed timetable; symptoms and recovery vary between people.

Common signs and factors linked with frozen shoulder
Common signs
- Gradual shoulder pain, often worse at night.
- Difficulty reaching overhead, out to the side or behind the back.
- Loss of both active and passive shoulder movement.
- Problems with dressing, grooming, sleep or household tasks.
Associated factors
- No clear trigger in many cases.
- Reduced shoulder movement after injury or surgery.
- Diabetes or thyroid conditions.
- Some neurological or other medical conditions.
Having one of these factors does not prove that you have frozen shoulder. A clinician may need to consider rotator-cuff problems, arthritis, neck-related symptoms, fracture, infection or other causes before recommending rehabilitation.

How physiotherapy may help
Physiotherapy aims to improve useful movement and function while respecting the shoulder’s current irritability. The NHS states that physiotherapy can help people regain movement in the shoulder. Read the NHS frozen shoulder guidance.
A plan may include education about the expected course, advice for sleep and daily tasks, gentle range-of-motion work, graded strengthening, posture or movement strategies and a home programme selected after assessment. Treatment intensity should change as symptoms change. Aggressive stretching or strenuous self-selected gym exercises may aggravate a highly painful shoulder, so more force is not automatically better.

What to expect at a first assessment
The physiotherapist will ask when symptoms started, what movements are limited, whether sleep is affected, and whether there was an injury, operation or period of immobilisation. Relevant medical history, including diabetes, thyroid conditions and current medical advice, should be discussed.
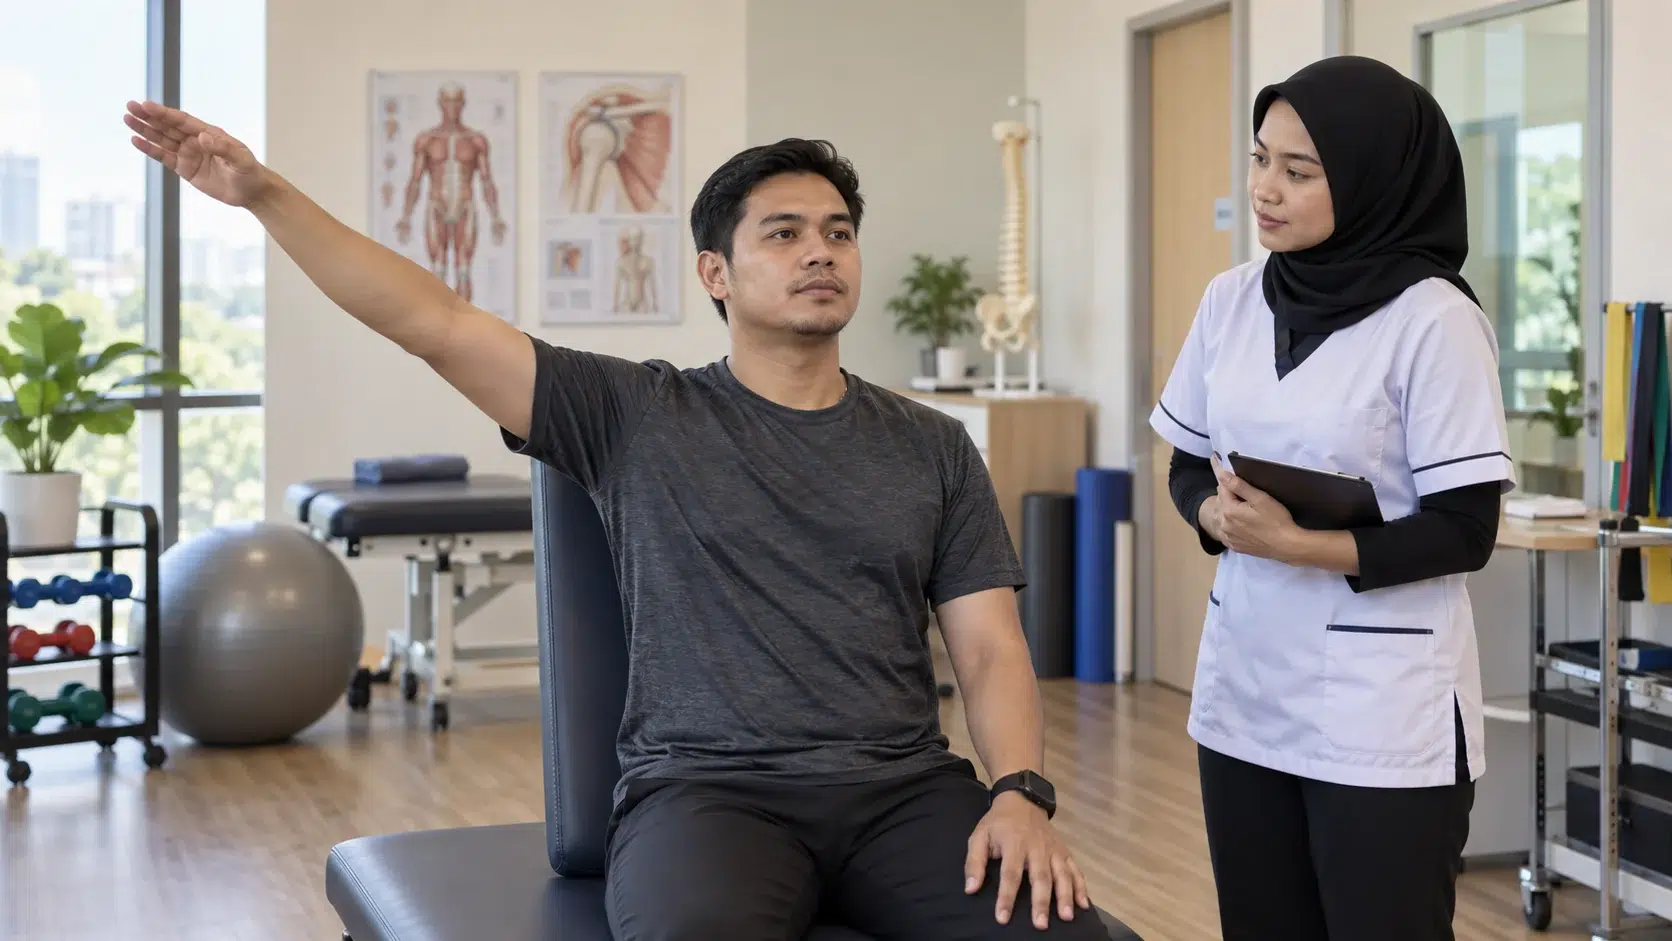
The physical assessment may compare both shoulders, observe active movement and gently examine passive movement, strength and function. Referral for medical review or imaging may be appropriate when the presentation is unusual, follows significant trauma or suggests another condition. The initial plan should focus on practical goals such as dressing, reaching or sleeping more comfortably.
Safe practical guidance
- Keep using the arm gently within a tolerable range instead of immobilising it without medical advice.
- Follow the exercise dosage given by your clinician; do not copy an advanced routine because it worked for someone else.
- Break demanding tasks into shorter periods and use the less painful hand where practical.
- Support the arm with pillows if that improves comfort at night.
- Report a clear worsening pattern or new symptoms rather than pushing through them.
When to seek medical care first
Arrange prompt medical assessment after a major fall or injury, with visible deformity, a suddenly unusable arm, a hot red swollen joint, fever, unexplained severe or worsening pain, new numbness or marked weakness, chest pain or breathlessness. These features are not typical self-management issues.
See a doctor or qualified clinician if persistent shoulder pain and stiffness are limiting movement or daily life. Physiotherapy does not replace medical assessment, injections, surgery or management of diabetes and other health conditions when those are clinically indicated.
Frequently asked questions
Can frozen shoulder get better?
Many people improve over time, but recovery can take months or years and is not identical for everyone. Assessment helps set realistic goals and identify other causes that may need different care.
Should I stretch through strong pain?
No. Exercise should be selected and progressed according to irritability and response. Strong pain, prolonged flare-up or loss of function is a reason to reduce the load and seek advice.
Do I need a scan?
Not everyone needs imaging to identify a typical frozen shoulder pattern. A doctor may request an X-ray, ultrasound or MRI when trauma, another diagnosis or a treatment decision needs clarification.
Can Physiomobile help at home or in a centre?
Physiomobile can check home or centre physiotherapy options after learning about your location, symptoms, medical history and mobility needs. Availability and suitability are confirmed during enquiry and assessment.
Related Physiomobile support
Learn about home physiotherapy or review the broader Physiomobile rehabilitation guide.
Discuss your shoulder rehabilitation needs
Share how long the pain and stiffness have been present, any injury or surgery, and the activities you want to regain. A physiotherapist can advise the next appropriate step after assessment.
Disclaimer: This page provides general education and does not diagnose frozen shoulder or replace medical advice. Treatment suitability depends on individual assessment.
